

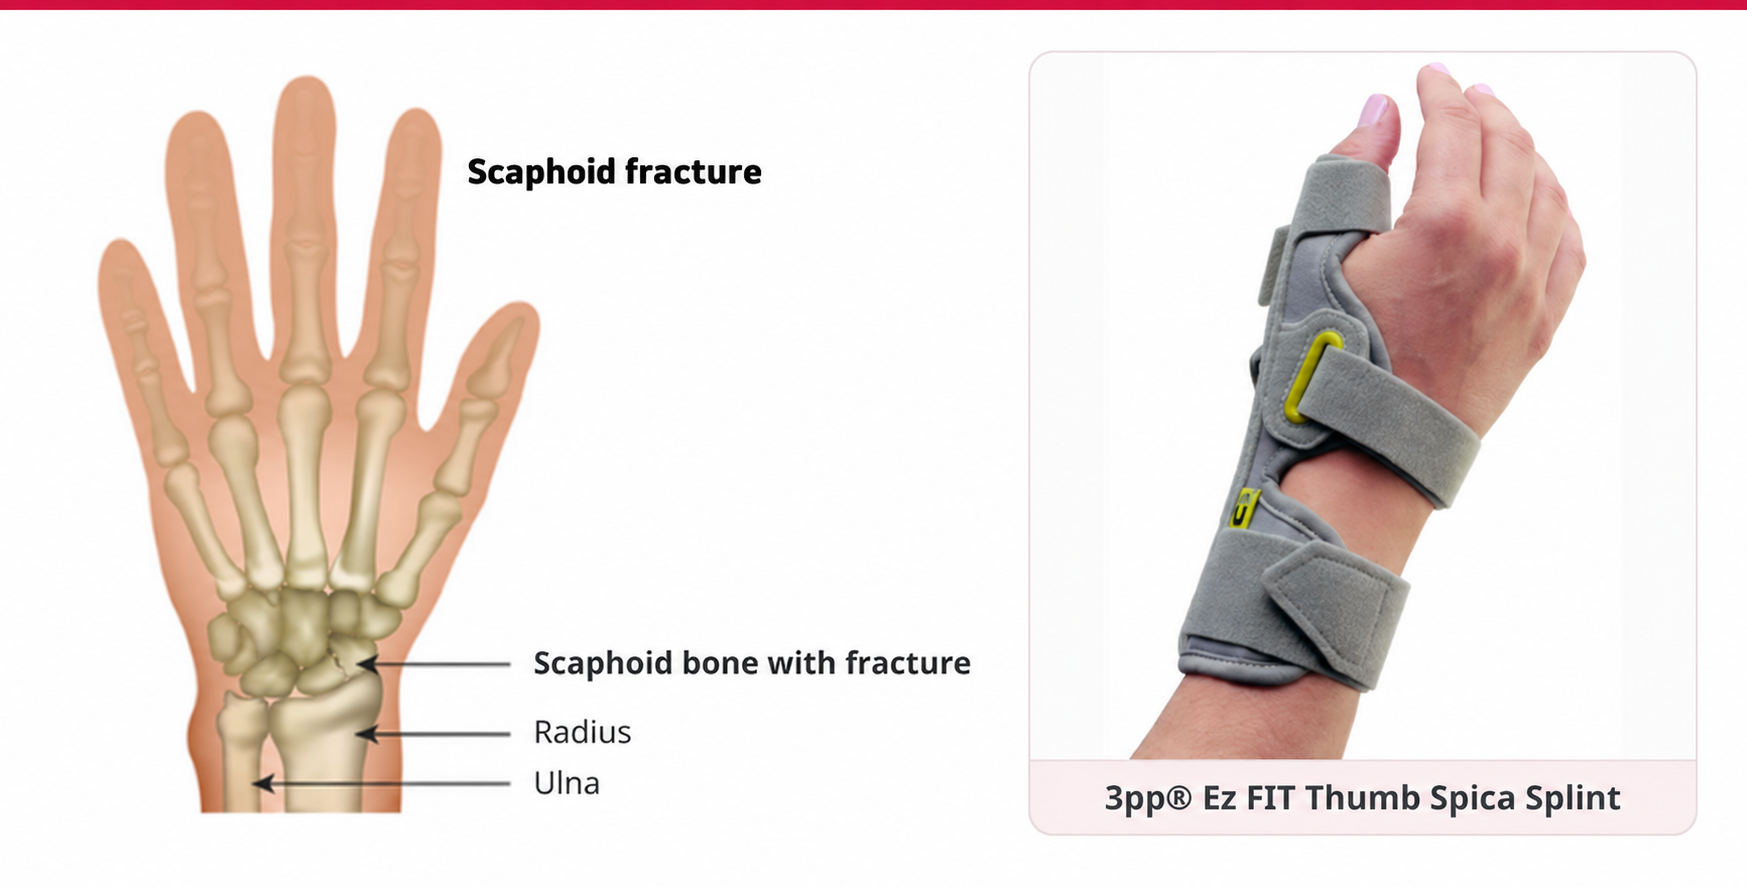
Scaphoid fractures commonly occur in young men and are often sustained when the wrist is forced into hyperextension during a fall onto an outstretched hand. The location and stability of the fracture help determine how long the wrist needs protection and when rehabilitation can begin.
Recognizing a Scaphoid Fracture
Patients often present with pain on the thumb side of the wrist, swelling, decreased range of motion, and tenderness in the anatomic snuffbox or over the scaphoid tubercle.
A scaphoid fracture may be difficult to see on initial radiographs. If a fracture is still suspected, immobilize the wrist in a splint and arrange prompt follow-up and further imaging. MRI can help detect an occult fracture, while CT is useful for assessing displacement and fracture healing.
Treatment Options of a Scaphoid Fracture
Treatment for a scaphoid fracture depends on its location, how stable it is, and whether it is healing as expected.
- Stable, nondisplaced waist or distal fractures. Fractures at the waist (mid-scaphoid) or distal scaphoid are often treated with thumb spica casting for 8–12 weeks.
- Proximal scaphoid fractures. A limited blood supply in this area can complicate or prolong healing. These fractures frequently require surgery with pin or screw fixation.
- Scaphoid nonunion. A fracture that has failed to heal is treated surgically with a bone graft and hardware fixation, followed by immobilization to allow healing.
Evaluation and Rehabilitation Following a Scaphoid Fracture
The therapy evaluation should include range of motion and strength testing as permitted by the treating physician, an edema measurement, and a pain rating. A patient-reported outcome measure such as the Patient-Rated Wrist Evaluation (PRWE) can help identify functional concerns. If proprioception is a concern after immobilization, joint position sense can be assessed once wrist motion is cleared by asking the patient to reproduce a wrist position without looking.
When a patient is referred to therapy while still in a cast or nonremovable orthosis, assess and address motion at the joints that are free to move, including the fingers, forearm, elbow, and shoulder, as permitted. Encourage light functional use within the patient’s restrictions and address edema as needed with elevation and gentle finger motion.
Once there is clinical healing on radiographs, the immobilization phase is usually over. Typically a Thumb Spica orthosis is then used for comfort and protection.
The 3pp Ez FIT Thumb Spica Splint is ideal for protection of the wrist and thumb following a scaphoid fracture The Ez FIT features include:
- Full-length aluminum stay can be contoured to position the wrist and thumb.
- Cushioned memory-foam lining adds comfort during wear.
- Adjustable straps help customize the fit.
- Open-finger design leaves the fingers free to move.
- Flat, low-profile buckles help keep straps from twisting for easier one-handed application.
- Fits either hand with one size that fits most.

A well-directed program of wrist and thumb range of motion can commence. It is important the patient is educated in the need for follow through with a documented exercise program and the knowledge that return to full range of motion and activities will take time.
The therapeutic program can be progressed as appropriate to include passive stretching and eventually strengthening exercises. Functional outcomes after a scaphoid are good, so therapy goals to return to functional motion and strength and everyday functional tasks are appropriate.


